Dr. Ward

Richard E. Ward, MD, MBA, CEO of Reward Health. Also physician, health care analytics and informatics innovator, husband, father, tenor & gradually improving swimmer

In response to a JAMA Viewpoint offering 4 principles for public health post COVID, I say yes, but we need a 5th principle – Science staying in its lane.

In a recent issue of JAMA, Daniel Morgan (U Maryland) and Deborah Korenstein (Icahn/Mt. Sinai) offered a viewpoint article that revisits the important evaluative conversation about the performance of our public health system during the COVID-19 pandemic and offers four useful principles for a “new approach to public health.” In this post, I will briefly

In response to a JAMA Viewpoint offering 4 principles for public health post COVID, I say yes, but we need a 5th principle – Science staying in its lane. Read More »

Health systems need to partner with universities to solve the inadequate supply of analytic talent

This week, I had the privilege of participating as a reviewer of a master’s thesis (“major project”) for a candidate for a master’s degree in economics at the University of Windsor.  The candidate’s project was a decision-analytic model that explored a patient’s decision to seek care and to pursue second opinions and the physician’s decisions

Health systems need to partner with universities to solve the inadequate supply of analytic talent Read More »

Time for a temporarily privatized CDC policymaking process, sponsored and funded by provider & payer organizations, professional societies and states.

Recent efforts by HHS Secretary Kennedy to politicize CDC policymaking leave us without the science-driven process the nation requires. Therefore, while we wait impatiently for the storm to pass, we will need a temporary arrangement where provider and payor organizations, professional societies and states cooperate to establish, fund and delegate some authority to a substitute

Time for a temporarily privatized CDC policymaking process, sponsored and funded by provider & payer organizations, professional societies and states. Read More »

Group meeting in front of complex diagram

Where Group Dynamics meets Analysis and Design: The importance of conceptual clarity and acknowledgement of complexity.

Groups matter When working as a consultant, leader, analyst or designer,  the work requires a mix of individual contributions and group contributions.  Group processes are required to (1) generate ideas, (2) vet ideas, and (3) achieve consensus, which is often a pre-requisite to buy-in and approval of initiatives to improve or build something. Group processes

Where Group Dynamics meets Analysis and Design: The importance of conceptual clarity and acknowledgement of complexity. Read More »

Trump/Musk killed AHRQ, but in a sense, the death has been playing out over 25 years. Recalling 4 eras of the agency and my dream for its eventual rebirth.

Slashing and Dissolving As reported by the Kaiser Family Foundation’s Health News site blog, last week the Trump administration “dissolved” the Agency for Healthcare Research and Quality (AHRQ), the agency that has for decades been at the center of the US Federal Government’s support for health services research in the service of improvement of our

Trump/Musk killed AHRQ, but in a sense, the death has been playing out over 25 years. Recalling 4 eras of the agency and my dream for its eventual rebirth. Read More »

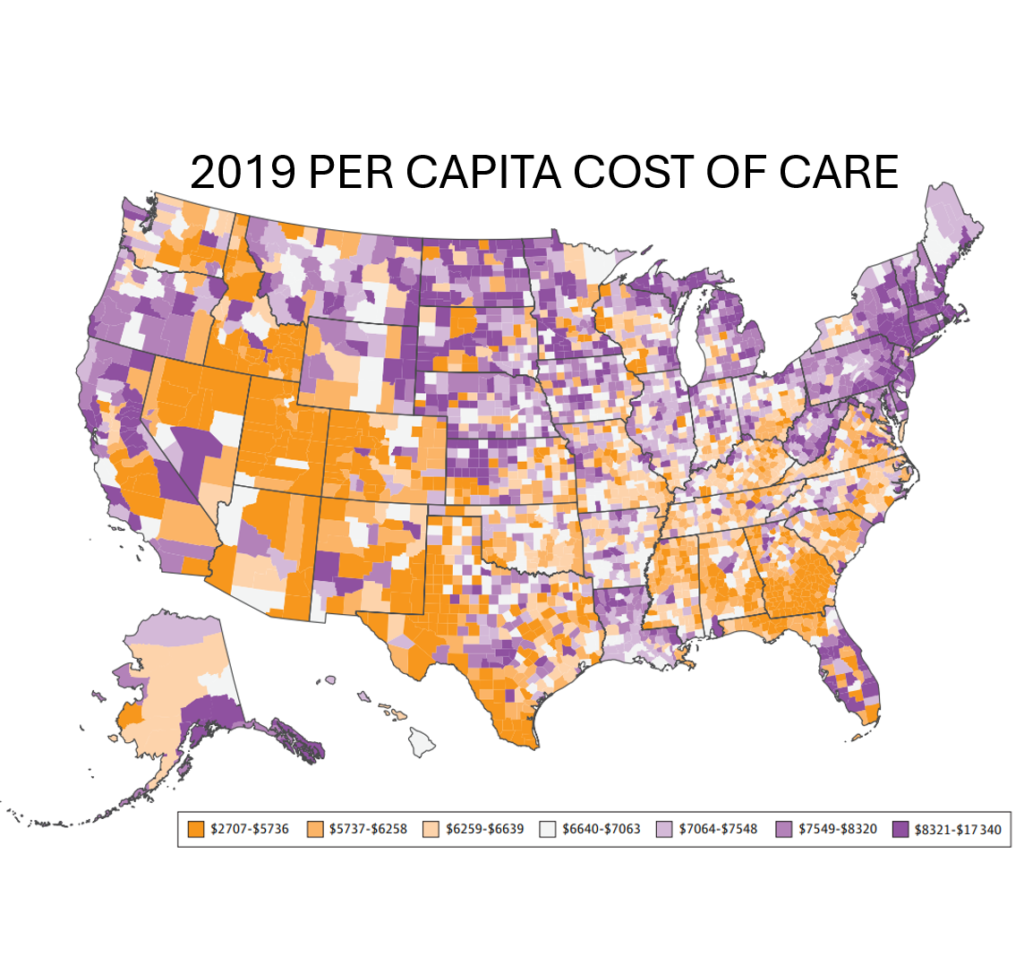
In the debate about price vs utilization as the main driver of geographic variation in cost of care, I say don’t get distracted from innovation.

I want to call your attention to a very thoughtful blog published by the semi-retired health care journalist, Merrill Goozner: the GoozNews Substack. Goozner’s most recent post, “It’s mostly overutilization, stupid” provides a delightful trip down memory lane, summarizing the decades-old debate about the causes of geographic variation in health care cost. Goozner started by

In the debate about price vs utilization as the main driver of geographic variation in cost of care, I say don’t get distracted from innovation. Read More »

image showing road with many lane markers

Recent nomination of anti-science leaders for HHS and CMS is a wake-up call. We need to defend science by staying in our lane to rebuild trust and objectivity.

The recent nominations of science-disrespecting people to lead HHS and CMS should be a wake-up call. Growing up, I naively believed that antipathy to science was relevant in Galileo’s time, but not modern times. Scientists as people were sometimes treated with disdain — as nerdy, awkward people wearing beanies with propellers, pocket protectors with slide-rules,

Recent nomination of anti-science leaders for HHS and CMS is a wake-up call. We need to defend science by staying in our lane to rebuild trust and objectivity. Read More »

Graph 2018 Total Low Value Services in MA compared to Traditional Medicare by Plan

Anthem and other Blue MA Plans are worse than traditional Medicare in use of Low Value Services

In the November 1, 2024 issue of JAMA, Ciara Duggan and others from Harvard and Brigham published a paper evaluating the utilization of “low value services” across major Medicare Advantage insurers and Traditional Medicare. Low value services utilization was defined based on the Choosing Wisely campaign and the US Preventive Task Force, and incorporated in

Anthem and other Blue MA Plans are worse than traditional Medicare in use of Low Value Services Read More »

Picture of studying for a test

Physicians want fewer quality measures, but more might be better if it motivates core process improvement rather than “studying for the test”

A JAMA study reports that PCPs are contractually held accountable for 57 unique quality metrics and asserts that is “oversaturation.” I have disagreed with the premise that we need fewer measures. On the contrary, I believe that we actually need a lot more measures to finally convince health care provider organizations to stop trying to “study for the test” and to actually learn the subject and improve the core processes that drive health care quality.

Physicians want fewer quality measures, but more might be better if it motivates core process improvement rather than “studying for the test” Read More »

The squeezing-the-balloon fallacy: Why savings from site-of-care shifts are wildly overestimated

The seemingly straightforward “grocery store” approach to calculating savings from health plans’ site of care shifting initiatives fails to account for fixed costs, a type of “squeeze the balloon” fallacy that leads to wildly exaggerated savings.

The squeezing-the-balloon fallacy: Why savings from site-of-care shifts are wildly overestimated Read More »